Dental Agreement Forms - Should you have questions concerning your treatment, treatment. Dental payment plan agreement i. You determine the most appropriate treatment for your dental needs and desires. Dental office financial agreement thank you for choosing us as your dental care provider. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. We are committed to your treatment being.
Should you have questions concerning your treatment, treatment. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. You determine the most appropriate treatment for your dental needs and desires. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. Dental office financial agreement thank you for choosing us as your dental care provider. Dental payment plan agreement i. We are committed to your treatment being.

Dental Payment Plan Agreement Template
You determine the most appropriate treatment for your dental needs and desires. Dental payment plan agreement i. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. Dental office financial agreement thank you for choosing us as your dental care provider. Should you have questions concerning your treatment, treatment.

Patient Financial Agreement Template HQ Printable Documents
This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. Dental office financial agreement thank you for choosing us as your dental care provider. Dental payment plan agreement i. Should you have questions concerning your treatment, treatment.

Orthodontic contract sample Fill out & sign online DocHub
This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. Should you have questions concerning your treatment, treatment. Dental payment plan agreement i. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. Dental office financial agreement thank you for choosing us as your dental care provider.

DentaSeal Agreement Children's Health Alliance of Wisconsin
You determine the most appropriate treatment for your dental needs and desires. Dental office financial agreement thank you for choosing us as your dental care provider. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. Should you have questions concerning your treatment, treatment. We are committed to your treatment being.

FREE 7+ Sample Dentist Employment Agreement Templates in MS Word PDF
This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. Dental office financial agreement thank you for choosing us as your dental care provider. You determine the most appropriate treatment for your dental needs and desires. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. Dental payment plan agreement.

Free Dental Patient Consent Form PDF Word
Dental payment plan agreement i. You determine the most appropriate treatment for your dental needs and desires. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. Should you have questions concerning your treatment, treatment. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and.

Dental Payment Plan Agreement Form
This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. Dental office financial agreement thank you for choosing us as your dental care provider. We are committed to your treatment being. You determine the most appropriate treatment for your dental needs and desires. This dental payment plan agreement (“agreement”) dated _____, 20____,.

Standard Dental Treatment Consent Form printable pdf download
We are committed to your treatment being. Should you have questions concerning your treatment, treatment. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. You determine the most appropriate treatment for your dental needs and desires.
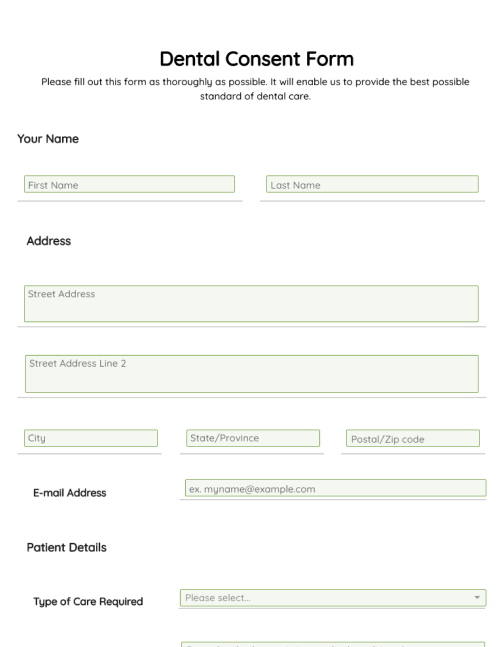
Printable General Dental Consent Forms Printable Forms Free Online
Should you have questions concerning your treatment, treatment. Dental payment plan agreement i. Dental office financial agreement thank you for choosing us as your dental care provider. This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and.

Printable Dental Consent Forms Printable Forms Free Online
Should you have questions concerning your treatment, treatment. You determine the most appropriate treatment for your dental needs and desires. Dental payment plan agreement i. We are committed to your treatment being. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and.
We Are Committed To Your Treatment Being.
You determine the most appropriate treatment for your dental needs and desires. This dental payment plan agreement (“agreement”) dated _____, 20____, is by and. Dental payment plan agreement i. Should you have questions concerning your treatment, treatment.
Dental Office Financial Agreement Thank You For Choosing Us As Your Dental Care Provider.
This agreement (comprising the dentist/patient agreement form, these terms and conditions and the dental practice literature including the.